Your Vascular Healthcare Partner
Need help with new product development?
Koven offers Product Design Consulting Services

What the Ankle Brachial Index Reveals About Peripheral Arterial Disease Severity 

September 1, 2026

A single ratio cannot capture every detail about limb circulation. However, the ankle brachial index remains one of the clearest starting points for understanding how severely peripheral arterial disease may be limiting blood flow. It compares systolic pressure at the ankle with systolic pressure at the arm. That simple relationship helps clinicians identify whether blood is reaching the legs normally, marginally, or at a clearly reduced level.

This is important because peripheral arterial disease is not always dramatic at first. Some people notice exertional leg discomfort. Others have subtle fatigue, slower recovery, or no obvious warning signs at all. This is one reason ABI testing is used for both symptomatic patients and people with significant vascular risk factors.

An ABI does more than support a diagnosis. It can give a clearer picture of the seriousness of impaired perfusion and helps frame what should happen next in evaluation and ongoing care.

Ankle Brachial Index: Why the Measurement Matters 

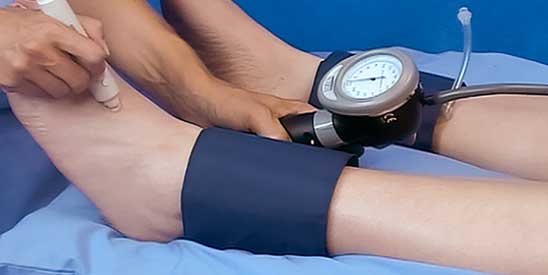
An ABI is a non-invasive, painless exam that uses blood pressure cuffs and a vascular Doppler to measure flow-related pressures in the arms and ankles. Since the test is quick and relatively straightforward, it has become widely used for early detection of PAD.

In a healthy limb, the ankle pressure will be close to the same as the arm pressure, which is why normal ABI values generally fall around 1.0 to 1.41. Once the ratio falls to 0.9 or below, PAD becomes much more likely, and progressively lower values point toward greater hemodynamic compromise. This is what makes the measurement so useful. It is not just identifying disease presence, it is also helping estimate the severity of disease.

1 Creager MA, et al. (2011). 2012 ACCF/AHA/ACR/SCAI/SIR/STS/SVM/SVN/SVS Key Data Elements and Definitions for Peripheral Atherosclerotic Vascular Disease: A Report of the American College of Cardiology Foundation/American Heart Association Task Force on Clinical Data Standards (Writing Committee to Develop Clinical Data Standards for Peripheral Atherosclerotic Vascular Disease). Circulation 2012, 125:395-467. Retrieved December 5, 2011 from http://circ.ahajournals.org/ content/125/2/395.

Why perform an ABI

How to Read the Range

ABI interpretation is valuable because the ranges broadly align with how compromised arterial flow may be. While the exact wording varies slightly across sources, the overall pattern is consistent.

  • 1.0 to 1.3 or 1.4. This range is generally considered normal, meaning ankle pressure is similar to or somewhat higher than arm pressure.
  • 0.9 to 1.0. This is often treated as borderline or acceptable, a zone where symptoms, history, and clinical suspicion still matter.
  • 0.7 to 0.9. This range commonly reflects mild PAD, suggesting reduced blood flow that may become more obvious with walking or exertion.
  • Below 0.4 or below 0.5. This level suggests severe PAD, where tissue perfusion may be poor enough to raise concern about wound healing and limb preservation.

    The practical lesson is simple. As the ABI decreases, concern about the adequacy of lower-extremity blood flow rises. A borderline result may support watchful follow-up and risk-focused management, while a markedly low value can signal the need for more urgent vascular assessment.

When One Number is Not Enough

Even though the ABI is highly useful, interpretation should never become mechanical. A high-value ABI, especially above 1.4, may point to stiff or calcified vessels that do not compress well under the cuff. This can create an artificially elevated result and make PAD harder to detect with ABI alone.

This issue is especially important in older adults and in people with diabetes, where arterial calcification is more likely to interfere with compressibility. In these settings, clinicians often need additional physiologic testing to get a truer picture of perfusion.

Ankle Brachial Index ankle pressure

A patient can have a concerning symptom pattern even when the ratio is only borderline.

A very high result does not always mean circulation is excellent. It may mean the vessels are too stiff for standard compression-based interpretation.

A severely low reading carries a different level of concern than a mildly abnormal one, particularly when ulceration or delayed healing is present.

Each value should be read alongside history, physical findings, and the clinical reason the test was ordered.

Ankle Brachial Index: Turning Results Into Clinical Direction

Once an ABI result is available, the question shifts from “Is PAD present?” to “What does this level of impairment mean for this person right now?”

This is where severity interpretation becomes truly useful. Mild disease may support close observation and broader cardiovascular attention, while moderate or severe findings often justify more comprehensive vascular evaluation.

The test itself is performed after rest in the supine position and relies on measured pressures from both brachial arteries and ankle arteries. It uses the ankle pressure divided by the highest systolic pressure taken at each arm.

Where Better Testing Supports Better Care

Used thoughtfully, the ABI remains one of the most clinically revealing ratios in vascular care. It helps connect symptoms, perfusion status, and disease severity in a format that is both measurable and actionable. Explore how Koven Technology supports ankle brachial index assessment and broader noninvasive vascular testing. Talk to us today.

Contact Us
Schedule a call
Koven logo

625 Maryville Centre Dr., Suite 300, St. Louis, MO 63141

© 2023 Koven Technology, Inc.
WBU-001 rev0